

FAQ SEARCH
What is CAR T-cell therapy?
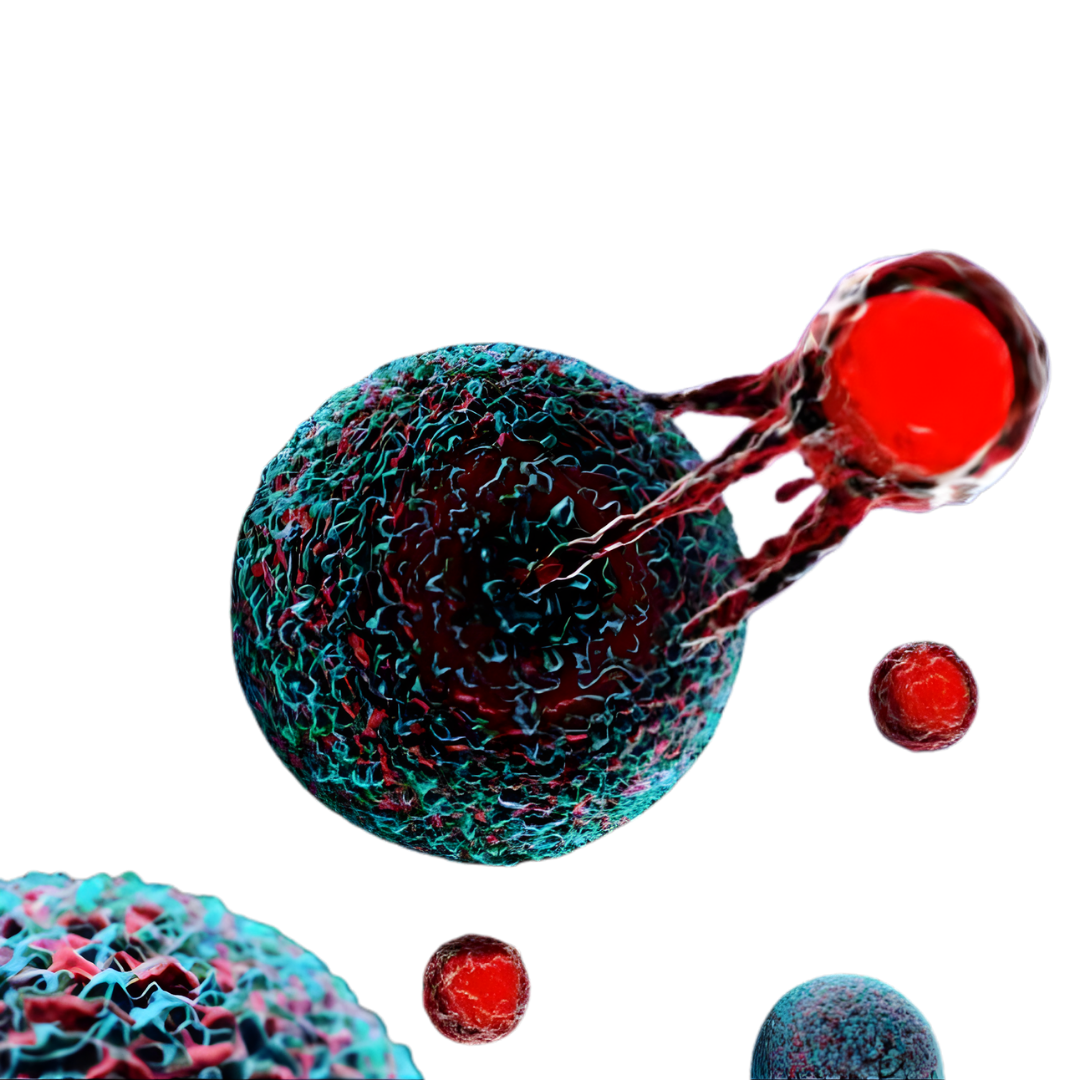
CAR T-cell therapy is an advanced immunotherapy in which a patient’s own T cells are genetically modified to better recognize and attack cancer cells, then reinfused back into the body.
Which cancers can be treated?
It is primarily used for certain blood cancers, including specific types of leukemia and lymphoma. It is FDA-approved and shows high response rates in eligible patients.
What is the success rate?
Success varies by cancer type, but in some forms of leukemia, response rates can reach up to 90% in eligible patients.
What are possible side effects?
Common side effects may include cytokine release syndrome (fever, fatigue), neurological symptoms, and temporary immune suppression. These are closely monitored by the medical team.
How long does the process take?
The full process — cell collection, laboratory modification, preparatory treatment, and infusion — typically takes several weeks.
Is there a new treatment for leukemia?
Yes. CAR-T therapy is a new immunotherapy approved by the FDA for relapsed leukemia with remission rates up to 90%.
Who is eligible for CAR-T therapy?
Patients with relapsed or refractory B-cell ALL, including children, young adults, and adults depending on clinical criteria.
Is CAR-T therapy safe?
Yes, but it may cause CRS and neurotoxicity, which are manageable with proper monitoring.
How long can remission last?
Some patients remain cancer-free for 4–6 years based on long-term follow-up of clinical trials.
How Much Does CAR-T Therapy Cost in 2025?
CAR-T treatment prices vary by center, product, and hospitalization needs. Most FDA-approved CAR-T therapies globally fall within $100,000–$190,000, excluding travel and supportive care.
Why Is CAR-T Therapy So Expensive?
CAR-T involves cell engineering, personalized manufacturing, and specialized hospital care—making the average price six figures worldwide.
Cost Comparison: USA vs Europe vs Turkey
The U.S. remains the most expensive market (up to $450K total package), while European centers offer $100–190K ranges. Türkiye remains competitive with lower facility costs.
Is CAR-T Therapy Worth the Cost?
When compared to survival rates and long-term remission data, many patients find CAR-T cost justified—especially after relapse post-chemotherapy or transplant.
What Determines CAR-T Therapy Price?
The final cost depends on cell processing, lymphodepletion chemo, ICU availability, CRS/ICANS management, and length of stay. Typical range: $100–190K.
Can Insurance Cover CAR-T Therapy?
Many countries partially reimburse CAR-T due to strong clinical outcomes. Some insurers cover up to 70–90% depending on diagnosis.
Affordable CAR-T Therapy Options
Emerging centers in Eastern Europe and Türkiye offer high-quality CAR-T programs within the $100K–$190K standard global range, easing financial burden.
FDA Approvals for CAR-T Therapy
The FDA has approved multiple CAR-T therapies for leukemia, lymphoma, and myeloma, marking a major breakthrough in cancer treatment.
Clinical Trials
Hundreds of clinical trials worldwide are exploring CAR-T therapy for both blood cancers and solid tumors, expanding the treatment potential.
Manufacturing CAR-T Cells
CAR-T cell manufacturing involves leukapheresis, genetic modification, cell expansion, and reinfusion into the patient.
What is TIL therapy?
TIL (Tumor-Infiltrating Lymphocyte) therapy is an immunotherapy approach in which a patient’s own immune cells are harvested, expanded in the laboratory, and reinfused to fight cancer.
Is TIL suitable for all cancer?
No. TIL therapy is currently used more commonly in certain solid tumors, especially metastatic melanoma. Suitability is decided upon individual evaluation.
What are the main advantages?
Its personalized nature and ability to strengthen the immune system in a solid-tumor targeted way are its primary advantages over general therapies.
Are there side effects?
Yes, including fever, fatigue, or temporary immune suppression. These are typically managed under expert medical supervision.
How long does it take?
The process, including cell expansion in the lab and preparatory regimens, usually takes 4-6 weeks.
Is TIL therapy FDA approved?
Lifileucel (Amtagvi) received accelerated FDA approval for advanced melanoma. Research continues for other tumor types.
What is immunotherapy?
Immunotherapy consists of treatments that stimulate or support the immune system to recognize and destroy cancer cells (e.g., PD-1 inhibitors, CAR-T, TIL).
What does targeted therapy mean?
Targeted therapies are drugs constructed to focus on specific molecular targets (mutations) in cancer cells, sparing normal cells more than chemotherapy.
Why is biomarker testing important?
It identifies DNA characteristics of the tumor to help doctors determine if a patient will benefit from specific targeted or immunotherapies.
What is a clinical trial?
Clinical trials test the safety and effectiveness of new treatments. They offer options when standard treatments are limited.
Difference: CAR-T vs TIL?
CAR-T cells are genetically engineered blood T-cells, whereas TILs are natural T-cells harvested directly from the tumor and expanded.
Why are these therapies expensive?
They are highly personalized, requiring complex GMP manufacturing, high-tech facilities, and specialized medical teams for a single patient's treatment.
What Is Included in the $100,000–$190,000 Package?
Patients often ask what this price covers: – Pre-testing – Cell collection – Manufacturing – Chemotherapy – Infusion – Hospital monitoring – CRS treatment
Is There a Cheaper Alternative to CAR-T? When Is CAR-T the Only Option?
For refractory leukemia/lymphoma, CAR-T remains the most effective therapy—alternatives rarely match remission rates.
Which Cancers Can CAR-T Treat?
CAR-T therapy is used for B-cell acute lymphoblastic leukemia, diffuse large B-cell lymphoma, multiple myeloma, and more.
How CAR-T Therapy Works CAR-T therapy works?
By engineering T cells to express chimeric antigen receptors that recognize and kill cancer cells.
How to manufacture CAR-T Cells?
CAR-T cell manufacturing involves leukapheresis, genetic modification, cell expansion, and reinfusion into the patient.
How long does it take for Car-T Cell Therapy?
CAR-T therapy process takes several weeks, from cell collection to infusion, requiring coordination and patient preparation.
How effective is TIL therapy?
Response rates range from 25–44% depending on cancer type, with long-term remission reported.
Is TIL therapy safe?
Side effects mainly stem from IL-2 and conditioning chemotherapy but are manageable in expert centers.
How long does TIL therapy take?
The process usually takes 4–6 weeks from tumor collection to infusion.
What are the main types of cancer treatment?
Surgery, radiotherapy, chemotherapy, immunotherapy, targeted therapy, hormone therapy, stem cell / bone marrow transplant, and supportive/palliative care.
What is the purpose of chemotherapy and what are its side effects?
Chemotherapy aims to kill rapidly dividing cancer cells; common side effects include nausea, hair loss, increased infection risk, and anemia
How does radiotherapy work?
It uses high-energy radiation to damage the DNA of tumor cells, killing them or stopping their growth. It is a localized treatment.
Is surgery used for every type of cancer?
No. Surgery is usually preferred in early-stage or localized cancers where the tumor can be removed. In metastatic or widespread disease, surgery may have limited benefit.
What is palliative care? Is it a treatment?
Palliative care focuses on relieving pain and other symptoms and improving quality of life. It can be given alongside life-prolonging treatments.
Why is molecular/biomarker testing important?
It identifies DNA or protein characteristics of the tumor to help determine which patients may benefit from targeted therapies or immunotherapies.
What is a clinical trial and why should patients consider joining one?
Clinical trials test the safety and effectiveness of new treatments. They can offer options when standard treatments are limited, but benefit is not guaranteed.
What is the difference between CAR-T cell therapy and TIL therapy?
CAR-T cells are genetically engineered from blood T cells to target specific antigens, whereas TILs are T cells taken directly from the tumor and expanded before being given back to the patient.
What is Lifileucel / Amtagvi?
Lifileucel (Amtagvi) is a TIL therapy in which tumor-derived T cells are expanded and given as a one-time infusion. It received accelerated FDA approval for advanced melanoma.
How effective is Lifileucel (Amtagvi)?
Studies supporting its approval reported an objective response rate of around 30%, with some patients experiencing durable, long-lasting responses.
What are the side effects of Lifileucel therapy?
Most side effects are related to pre-infusion chemotherapy and high-dose IL-2, including anemia, fever, low platelets, and neutropenia. Cytokine release syndrome and neurotoxicity are reported less frequently than with CAR-T therapies.
Why are these cellular therapies so expensive?
Because they are personalized, require complex manufacturing, high-tech one-time procedures, and specialized facilities, which significantly increase costs.
Who may be eligible for TIL therapy?
Typically, patients with good overall health, adequate heart and lung function, and advanced melanoma who have already received certain immunotherapies or targeted therapies. Eligibility varies by center and protocol.
Why are combination therapies used in cancer treatment?
To increase effectiveness, delay resistance, and improve tumor shrinkage by using different mechanisms of action (e.g., immunotherapy plus targeted therapy).
In which cancers is immunotherapy particularly effective?
Melanoma, certain types of lung cancer, and MSI-high/MMR-deficient colorectal cancers are among those that tend to respond well, with the range of indications continuing to expand.
What are antibody–drug conjugates (ADCs)?
They are targeted therapies in which a cytotoxic drug is attached to an antibody that specifically recognizes cancer cells, allowing more selective delivery of treatment.
How are side effects managed?
Management depends on the treatment and may include anti-nausea drugs, growth factors, blood products, steroids, and close monitoring by a multidisciplinary team.
Are early-stage cancers always curable?
Many early-stage cancers are treated with curative intent, but outcomes depend on cancer biology, treatment type, and patient factors, so cure cannot always be guaranteed.
What is the goal of treatment in metastatic cancer?
The goals are usually to control the disease, relieve symptoms, and improve or maintain quality of life. Some patients may experience long-term response.
What do adjuvant and neoadjuvant therapy mean?
Adjuvant therapy is given after surgery to reduce the risk of recurrence, while neoadjuvant therapy is given before surgery to shrink the tumor.
How important is genetic testing for family members?
If inherited mutations (such as BRCA or Lynch syndrome) are found, both treatment decisions and cancer screening strategies for family members may change.
How is cancer treatment different in older adults?
Treatment is tailored based on comorbidities, functional status, and tolerance, with dose adjustments and enhanced supportive care.
When is bone marrow / stem cell transplantation needed?
It is often used in some blood cancers after high-dose chemotherapy, but its role is limited in solid tumors.
What does “residual disease” mean in cancer treatment?
It refers to microscopic or small remaining cancer cells after treatment, which may require additional therapy or close follow-up.
When should patients be referred to palliative oncology?
Palliative care can be introduced from the time of diagnosis if there are symptoms or quality-of-life concerns, and early referral is recommended.
Can immunotherapy cause delayed side effects?
Yes. Immune-related side effects affecting the skin, thyroid, colon, liver, lungs, and other organs can occur later and may require long-term monitoring
How does treatment resistance develop?
Cancer cells can acquire mutations, activate alternative signaling pathways, or lose drug targets, which is why combination therapies and new agents are continuously researched.
Where can treatment options for rare cancers be found?
NCCN and ASCO guidelines, specialized cancer centers, expert oncologists, and clinical trials are the most up-to-date sources. Referral centers are often recommended.
What are late complications after radiotherapy?
They may include local tissue stiffening, fibrosis, organ dysfunction, and a small risk of secondary cancers, depending on the radiation area
Why is rehabilitation (physical and psychological) important in cancer care?
It helps restore function, manage fatigue, provide psychological support, and improve overall quality of life through a multidisciplinary approach.
In which situations can immunotherapy fail?
It may be less effective if the tumor microenvironment is immunosuppressive, the target antigen is absent, or the patient’s immune system is weak.
Are targeted drugs available for every patient?
No. They can only be used when a specific molecular target or mutation is present, which is why molecular testing is required.
How does post-treatment surveillance work?
It involves scheduled clinical exams, imaging tests, and sometimes tumor markers, according to cancer-specific guidelines.
What is the role of nutrition and exercise in cancer care?
Proper nutrition helps manage symptoms, and regular physical activity reduces fatigue and improves quality of life, but plans should be individualized.
Should fertility preservation be considered before treatment?
Yes. Options such as sperm, egg, or tissue preservation should be discussed before chemotherapy or radiotherapy that may affect reproductive function.
How are new options found for resistant or recurrent cancers?
Through clinical trials, molecular-based treatment selection, and combination strategies, usually by consulting specialized oncology centers.
How are tumor measurements and response evaluated?
Responses are typically assessed using imaging-based criteria such as RECIST, although immunotherapy can show different response patterns.
How do costs and insurance affect cancer treatment?
Costs vary widely based on drugs, facilities, and production processes. Some new cellular therapies are very expensive, and insurance coverage depends on country and policy.
How are advanced targeted agents and immunotherapies approved?
They are approved through regulatory pathways (such as the FDA) after clinical trials demonstrate safety and effectiveness, sometimes under accelerated approval programs.
What does “personalized/precision medicine” mean in cancer care?
It means selecting treatments based on the molecular characteristics of an individual patient’s tumor, often involving targeted drugs and immunotherapies.
Who are the members of the cancer care team?
Medical oncologists, surgeons, radiation oncologists, nurses, palliative care specialists, dietitians, physical therapists, social workers, and clinical research staff.
How is life expectancy estimated in advanced cancer?
It varies greatly depending on cancer type, response to treatment, overall health, and tumor biology, and giving a single number is often misleading.
How can patients learn about new treatment opportunities?
By following ClinicalTrials.gov, cancer center teams, patient advocacy groups, and guideline-issuing organizations such as ASCO or NCI.
Why might a treatment plan change?
Lack of response, unacceptable side effects, new test results, or patient preferences can all lead to changes in the treatment plan.
Where can drug approvals and “label” information be found?
On the websites of regulatory agencies such as the FDA and EMA, which publish approval letters, prescribing information, and review documents.
How can infection risk be reduced during treatment?
Through neutropenia management, sterile procedures, antiviral/antibiotic protocols, and patient education.
What is the difference between clinical trial results and real-world data?
Clinical trials use selected patient groups and strict protocols, whereas real-world data reflect more diverse patient populations and everyday clinical practice.
What are the future trends in cancer treatment?
Expansion of cellular therapies to solid tumors (e.g., TIL approvals), immunotherapy combinations, antibody–drug conjugates, personalized vaccines, and improved biomarker-driven treatment strategies.